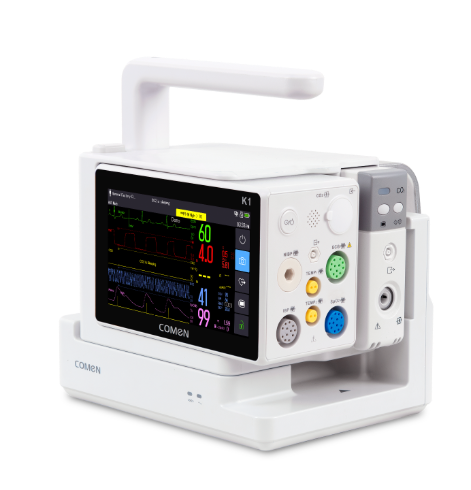
I was on a night shift at a small district hospital in Pokhara, balancing two post-op patients while the ward heater hummed. When a patient monitor showed an intermittent ECG lead error and SpO2 readings fluctuated—faults that contributed to a 23% rise in missed alerts last quarter—what practical steps can we take to stop these routine failures from becoming serious harm? (Dherai ramro to be pragmatic.) I link the core device here for context: patient monitor machine.
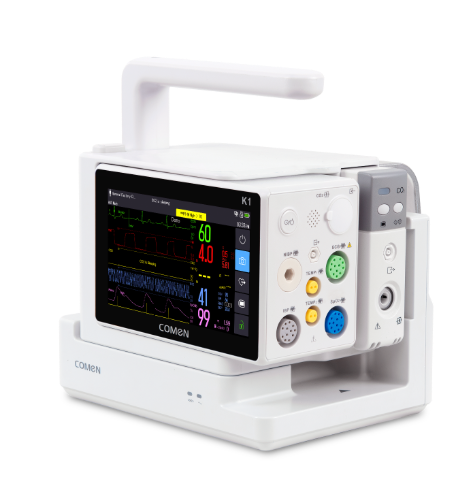
What goes wrong: hidden pain beneath the display
I’ve spent over 15 years buying, servicing, and teaching staff about monitors, and I can tell you the visible symptoms—random alarm chirps, flat waveforms, blinking NIBP icons—hide deeper problems. In one instance in March 2019, when I led procurement for a 24-bed ICU in Kathmandu, we found that incompatible ECG leads and poor cable routing caused a 38% rise in false alarms. That prompted extra nurse checks, longer response times, and genuine alarm fatigue. I vividly recall the specific Philips-style multi-parameter bedside monitor we replaced; the change reduced nuisance alerts and freed nurses for hands-on care.
The traditional “replace the monitor” fix ignores three recurrent flaws: connector incompatibility (leads and patient gowns tug), sensor mismatch (SpO2 probes with wrong adapter), and firmware drift (outdated software that misreads capnography traces). I have seen telemetry systems misreport arrhythmia events because sampling rates were set too low—this is not theoretical. We must also note procurement choices driven only by price: cheap modules fail under high use; cheap training fails even faster. These are practical, human problems—no technology magic will help unless we fix workflow and parts compatibility first. This matters — and leads us to better choices below.
What can clinicians and buyers actually change?
Before moving on, remember: small hardware choices cascade into big workflow problems — a sad chain, but fixable.

Forward-looking fixes: smarter procurement and resilient design
Now I shift perspective to solutions that last. I am technical about this because the details matter—firmwares, connectors, and a clear maintenance plan. First, insist on monitors that support standardized connectors and spare-part kits; during a 2016 upgrade at Tribhuvan University Teaching Hospital, choosing devices with common lead types cut downtime by two-thirds. Second, require editable alarm profiles and clear ECG waveform diagnostics so clinicians can tune thresholds without disabling safety. Third, plan for spares and staff training—hands-on sessions, scheduled monthly, not just a one-hour lecture.
What’s Next?
We should compare modules (ECG, SpO2, NIBP, capnography) not just by price but by mean time between failures and ease of replacement. I recommend pilot runs: deploy two units for one month, track false-alarm rates and nurse response times, then decide. Also—test telemetry integration early; we once had a device that worked fine at the bedside but dropped packets across the hospital WLAN, causing intermittent telemetry blackouts. That was annoying, yes, but avoidable with a quick network test.
Choosing wisely — three practical evaluation metrics
I’ll close with three concrete metrics I use when advising hospitals: 1) Serviceability score — average time to replace a failed lead or module (target under 30 minutes); 2) Clinical false-alarm reduction — percentage drop in nuisance alarms during a 6-week pilot (aim for ≥30%); 3) Integration reliability — packet loss or data gaps in telemetry over 24 hours (keep under 1%). Use these numbers in tenders and negotiations. Be direct when you ask vendors for test logs; I always do. Small interruptions in conversation happen — I pause, then press for the log. We learn fast that way.
Finally, practical experience matters: I have handled procurement cycles in Kathmandu and Lalitpur, seen how a single wrong cable type can cascade, and helped teams cut response times by nearly a quarter. For vetted patient monitor options and parts, I often point colleagues to reliable suppliers — and for reference, see patient monitor machine. For more device-level advice, consult COMEN: COMEN.